Basics
What is an ileostomy?
An ileostomy brings the end of the small intestine through the abdomen, so stool collects in a pouch. Why it's created, output, diet and reversal.
On this page
- What is an ileostomy?
- Where does an ileostomy sit in the digestive tract?
- How an ileostomy differs from a colostomy
- How an ileostomy differs from a urostomy
- Why is an ileostomy created?
- Inflammatory bowel disease
- Inherited polyp syndromes and bowel cancer
- Protective (defunctioning) ileostomies
- Other reasons
- Choosing between an ileostomy and an internal pouch
- End ileostomy vs loop ileostomy
- End ileostomy
- Loop ileostomy
- Which type will I have?
- What does an ileostomy look like?
- Why the stoma is usually on the lower right
- The spout and why it matters
- How the stoma changes over time
- How is ileostomy surgery performed?
- Before the operation
- During the operation
- Recovery in hospital
- What does ileostomy output look like?
- The first days after surgery
- Established output
- High-output ileostomy
- Hydration and electrolytes: the biggest practical change
- Why the colon matters
- What good hydration looks like
- Oral rehydration solutions
- Signs of dehydration to act on early
- Diet and eating with an ileostomy
- Reintroducing food after surgery
- Foods that may cause a blockage
- Foods that may thicken output
- Foods that may loosen output
- Gas and odour
- A note on fibre and fluids together
- Pouching, emptying and skin care
- How often to empty and change
- Keeping the skin healthy
- When pouching gets difficult
- What complications should I be aware of?
- Peristomal skin irritation
- Food blockage
- Parastomal hernia
- Prolapse, retraction and stenosis
- Dehydration and electrolyte imbalance
- Kidney injury
- Vitamin B12 deficiency
- Gallstones and kidney stones
- When to seek medical help
- Living with an ileostomy
- The daily routine
- Clothing
- Showering, swimming and bathing
- Exercise and sport
- Travel
- Sex and intimacy
- Work
- Emotional wellbeing
- Reversal: when ileostomies are temporary
- What reversal involves
- After reversal
- Support and community
- The bottom line
An ileostomy is a surgical opening (a stoma) that brings the end of the small intestine — the ileum — through the abdominal wall, so stool leaves the body into a pouch on the skin rather than passing through the colon, rectum and anus. Because the large intestine is bypassed, output is looser and more frequent, and staying well hydrated becomes the main daily priority. An ileostomy may be temporary or permanent.
Ileostomies have transformed care for diseases that were once disabling or fatal, particularly severe inflammatory bowel disease (ulcerative colitis and Crohn’s disease) and familial adenomatous polyposis (FAP). Today, with modern pouching systems and good education, most people with an ileostomy work, travel, exercise and raise families without major restriction.
This guide explains what an ileostomy is, why it might be created, how the surgery works, what daily life looks like, and where to get reliable support. It is general information only — your own stoma care nurse or surgical team is the right place for advice about your situation.
What is an ileostomy?
An ileostomy is a deliberate opening made between the inside of the bowel and the outside of the body. During surgery, the surgeon divides the small intestine and brings the cut end out through a small opening in the abdominal wall. The bowel is then turned back on itself, like a cuff, and stitched to the skin. The result is a stoma: a soft, moist, pink-red button of bowel tissue about 2–3 cm across that sits just proud of the abdominal surface.
Stool now leaves the body through the stoma rather than travelling onwards through the colon, rectum and anus. Waste is collected in a lightweight pouch that sticks to the skin around the stoma. Nothing about the stoma is voluntary — there is no sphincter muscle — so the pouch is worn continuously and emptied when it is about a third to half full.
The word comes from ileum, the final section of the small intestine, and -stomy, meaning an opening. A person may have an ileostomy even if their entire colon is still present, for example when a temporary loop ileostomy is used to protect a fresh surgical join further down.
Where does an ileostomy sit in the digestive tract?
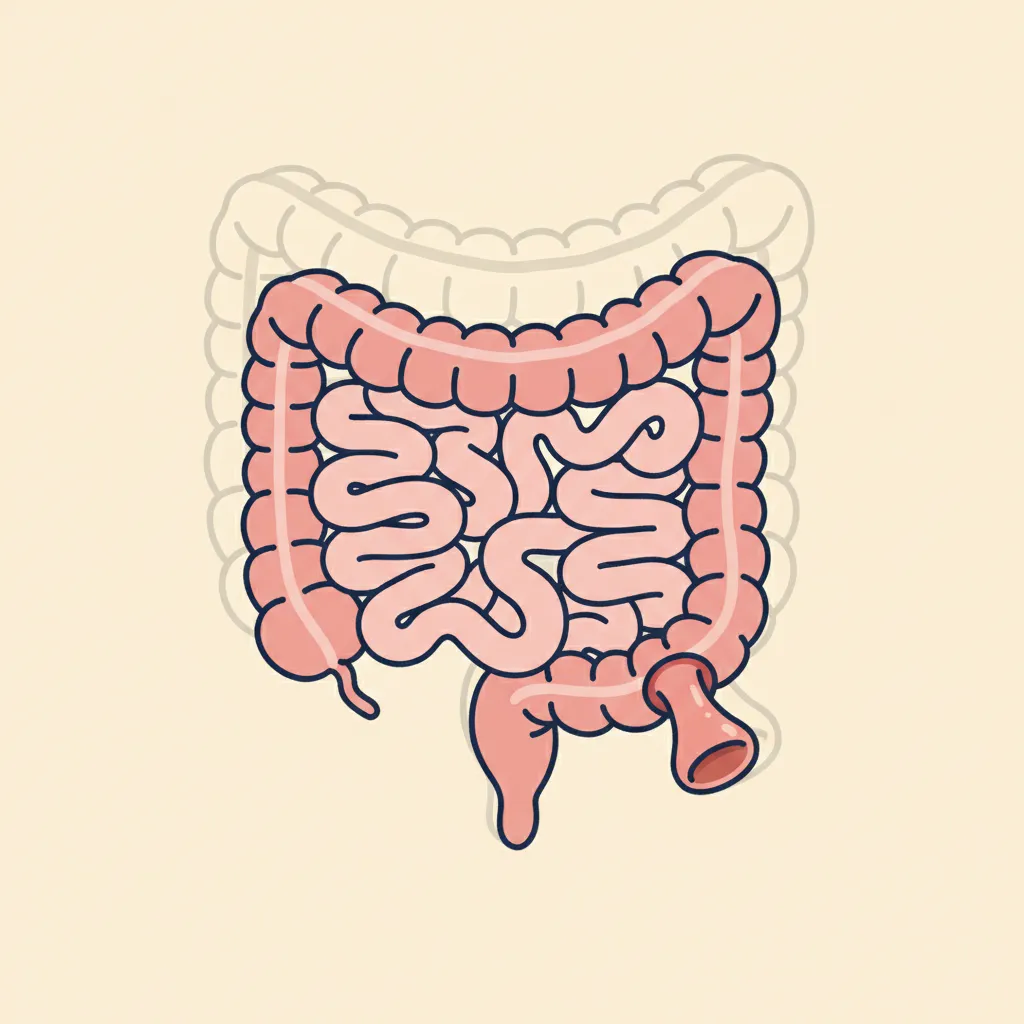
The small intestine has three parts: the duodenum, the jejunum and the ileum. Food leaves the stomach, is digested and absorbed along the jejunum and ileum, and then normally passes into the colon (large intestine), where water, sodium and other electrolytes are reclaimed and stool is stored and formed.
An ileostomy is usually created in the last part of the ileum, close to where it would have joined the colon. Digestion and absorption of protein, fat, carbohydrate, most vitamins and most minerals continue largely as before, because the stomach and the upper small intestine are untouched. What is lost is the colon’s work: the reabsorption of roughly a litre or more of fluid each day, along with sodium, chloride, potassium and bicarbonate, and the slow storage that turns liquid effluent into a formed stool.
That single anatomical difference explains most of what makes ileostomy care distinctive: loose output, frequent emptying, and a lifelong need to think about fluid and salt.
How an ileostomy differs from a colostomy
Both are bowel stomas, but they behave very differently. A colostomy uses part of the colon, is usually sited on the left side of the abdomen, and generally produces a semi-formed or formed stool that is emptied one to three times a day. Because the colon has already absorbed most of the water, dehydration is far less of a concern, and many colostomies can be managed with irrigation (a controlled washout) or a closed pouch.
An ileostomy sits on the lower right side, produces liquid to porridge-thick output several times a day, and requires a drainable pouch. It cannot be irrigated. Hydration, skin protection from enzyme-rich output, and blockage risk are the recurring themes.
How an ileostomy differs from a urostomy
A urostomy diverts urine, not stool. It is created when the bladder must be removed, and uses a short segment of bowel as a conduit from the kidneys to the skin. The stoma looks similar, but the output is urine, the pouch has a tap rather than an open end, and the care priorities are different — preventing urinary infection and protecting skin from alkaline urine. Ileostomy and urostomy are sometimes grouped together as ‘ostomies’, but they are not interchangeable.
Why is an ileostomy created?
An ileostomy is created when the colon or rectum is too diseased, damaged or absent to safely handle stool, or when stool needs to be diverted away from a healing join. The most common reasons are listed below.
Inflammatory bowel disease
Ulcerative colitis affects only the colon and rectum. When medicines fail, when the disease becomes steroid-dependent, or when complications such as toxic megacolon or precancerous change develop, removing the colon becomes the definitive treatment — and that means a stoma of some kind. Crohn’s disease can affect any part of the gut, so surgery is used more sparingly and is tailored to the diseased segment; some people with Crohn’s will have an ileostomy at some point.
Inherited polyp syndromes and bowel cancer
Familial adenomatous polyposis (FAP) causes hundreds of polyps in the colon and carries a near-certain risk of cancer without surgery. Removing the colon and rectum is standard, and an end ileostomy or an internal pouch is then a choice. Colorectal cancer may require an ileostomy when the whole colon and rectum are removed, or temporarily when a low join needs protection.
Protective (defunctioning) ileostomies
After surgery that joins two ends of bowel together (an anastomosis) low in the pelvis, a loop ileostomy is often created upstream. Stool is diverted away from the join while it heals, which reduces the consequences if a leak occurs. This is one of the commonest reasons for a temporary ileostomy.
Other reasons
Severe trauma, perforation, radiation damage to the pelvis, and motility disorders such as chronic intestinal pseudo-obstruction may all lead to an ileostomy. In children, congenital conditions such as Hirschsprung’s disease or necrotising enterocolitis may occasionally require one.
Choosing between an ileostomy and an internal pouch
When the colon and rectum must both be removed, many people are offered a choice between a permanent end ileostomy and an internal pouch — also called a J-pouch or ileal pouch–anal anastomosis (IPAA) — in which a reservoir is fashioned from the small intestine and joined to the anus so stool leaves the body in the usual way. An internal pouch avoids a stoma but usually means four to eight bowel movements a day, a risk of pouchitis, and a more complex operation. Some people are not suitable candidates for a pouch. Both routes are well established; the right choice is highly individual and best discussed with your surgical team.
End ileostomy vs loop ileostomy
There are two main configurations, and they behave differently.
End ileostomy
The cut end of the ileum is brought through the abdominal wall and turned back on itself to create a small spout. This is used when the colon, rectum or both have been removed — for example proctocolectomy with end ileostomy. End ileostomies are usually permanent, are generally easier to fit a pouch to because of the spout, and tend to settle into a stable size within a few months.
Loop ileostomy
A loop of small bowel is lifted to the surface and opened, producing a stoma with two openings side by side. One limb (the proximal limb) passes stool; the other (the distal limb) usually passes only mucus, which is normal and not a sign of disease. Loop ileostomies are usually temporary, designed to be reversed once the downstream join has healed. They are quicker to construct and to reverse than end ileostomies, but they can be slightly more awkward to pouch, sit flatter, and are more prone to prolapse and to high output in the early weeks.
Which type will I have?
This depends almost entirely on what else is being done. If the colon and rectum are coming out, you will have an end ileostomy. If the bowel below is staying and simply needs protecting while it heals, you will have a loop ileostomy. Occasionally a double-barrelled or separated stoma is used, in which the two ends are brought out as separate openings.
What does an ileostomy look like?
A stoma is a small, round or oval section of bowel, about 2–3 cm across, that sits just above the skin and looks like the inside of your cheek: pink to red, moist, and well supplied with blood. It has no nerve endings, so it does not hurt to touch or clean — many people are surprised by this. It may bleed a tiny amount when wiped, which is normal for bowel lining.
Immediately after surgery the stoma is swollen, and it shrinks steadily over the following six to eight weeks as the swelling settles. It may be round at first and become oval later. Small changes in size mean the pouch opening needs re-measuring regularly in the early months.
Why the stoma is usually on the lower right
The ileum naturally sits on the right side of the abdomen, and a stoma on the lower right can usually be brought out without tension on the bowel. Wherever possible the site is chosen before surgery by a stoma care nurse, with the patient sitting, standing and lying down, so that it sits on flat skin, is easy to see and reach, and avoids creases, scars, the waistband, the bony pelvis and the umbilicus. Good site selection is one of the strongest predictors of long-term comfort and fewer complications.
The spout and why it matters
An ileostomy is usually built to protrude slightly — a ‘spout’ of 1–2 cm. This is deliberate: it lets liquid output drop cleanly into the pouch rather than tracking under the adhesive and onto the skin. It matters because ileostomy output is rich in digestive enzymes and is alkaline, so even small, repeated leaks can break the skin down quickly and painfully.
How the stoma changes over time
Over months and years the stoma may become slightly flatter or develop a different shape, particularly with weight change. A flatter stoma, or one that sits below the level of surrounding skin, may need a different style of pouching system — something your stoma care nurse can assess.
How is ileostomy surgery performed?
Ileostomy surgery is carried out under general anaesthetic. It can be performed:
- Open — through one larger abdominal incision
- Laparoscopically — through several small incisions with a camera (keyhole surgery)
- Robotically — a variation of laparoscopic surgery using a surgical robot
The approach depends on what else is being done, your body shape, and your surgeon’s preference and experience. A purely defunctioning loop ileostomy in a relatively well patient may take one to two hours; a total proctocolectomy with end ileostomy for severe ulcerative colitis or FAP can take four to six hours.
Before the operation
Wherever possible the stoma site is marked on the abdomen beforehand. Pre-operative assessment also covers blood tests, anaesthetic review, and — for people with inflammatory bowel disease — optimisation of nutrition and medication, since being as well as possible before surgery reduces complications.
During the operation
The surgeon removes or bypasses the diseased bowel, brings the ileum to the surface, and constructs the stoma. If a pouch or a join is being made at the same time, that is completed before the stoma is fashioned. A clear plastic or transparent pouch is usually fitted in theatre so the stoma can be monitored closely in the first day or two.
Recovery in hospital
Most people stay in hospital for four to ten days, depending on the type of surgery and how recovery progresses. In the first day or two you will be encouraged to sip fluids, then build up to light food. Pain relief, early movement and breathing exercises all help prevent complications. Your stoma nurse will teach you to empty, change and order your supplies before you go home, and will usually arrange follow-up.
What does ileostomy output look like?
Before surgery, many people are anxious about what the stoma will produce. In practice it follows a fairly predictable pattern.
The first days after surgery
Once the bowel ‘wakes up’ after the anaesthetic and surgical handling — usually after two or three days — output begins. It typically passes through three phases:
- The first day or two: mostly gas and clear or greenish fluid
- The next few days: thin, dark liquid
- Within one to four weeks: porridge or oatmeal consistency, mid-brown to yellow-brown
Established output
A well-functioning long-term ileostomy produces roughly 500–1,200 mL of output a day, emptied around four to eight times. Output is usually looser after meals and quieter overnight, although it is never entirely predictable. What you eat, how much you drink, your medicines and any illness all shift it.
High-output ileostomy
Output of more than about 1,500–2,000 mL per day is recognised as high-output ileostomy. It matters because it can quickly lead to dehydration, low sodium, low magnesium and kidney strain, and it is one of the commonest reasons for readmission in the first weeks after surgery. Causes include infection, blockage, some medicines, abrupt changes in diet, and short bowel. High output that persists beyond a day or two needs medical review rather than home adjustment.
Hydration and electrolytes: the biggest practical change
If there is one thing that separates life with an ileostomy from life with a colostomy, it is fluid balance.
Why the colon matters
The colon normally reabsorbs about a litre of water and a substantial amount of sodium every day from the fluid delivered to it by the small intestine. After ileostomy surgery, that reclamation does not happen: fluid and salt leave the body in the pouch instead. People with an ileostomy therefore need more fluid and, usually, a little more salt than the average person.
What good hydration looks like
General principles that most stoma teams share:
- Drink more than you would have before surgery — commonly in the region of two litres or more a day in normal conditions, and more in hot weather, during exercise, or when output is high
- Sip steadily through the day rather than drinking large volumes in one go, which tends to increase output rather than improve hydration
- Do not restrict salt unless a doctor has told you to for another reason such as heart or kidney disease
- Use urine colour as a rough guide — pale straw suggests good hydration; dark amber suggests you need more fluid
- Be alert after vomiting, diarrhoea, hot weather, air travel and strenuous exercise, all of which raise requirements
The exact volume that suits you depends on your stoma, your output, your kidneys and any other conditions, so your own target should come from your stoma care nurse or clinician rather than from a general figure.
Oral rehydration solutions
Plain water alone is not always enough when output is high. In that situation, large volumes of plain water can dilute the body’s sodium further and make things worse. Oral rehydration solutions — balanced glucose-and-salt mixtures available on prescription or recommended by your team — are absorbed more effectively and are the mainstay of managing high output. Many stoma teams provide a written plan for exactly when and how to use them. Ask your nurse which product and plan is right for you before you need it.
Signs of dehydration to act on early
- Dark, strong-smelling urine, or passing very little urine
- Dizziness or light-headedness on standing
- Headache, dry mouth, thirst that is not relieved by drinking
- Muscle cramps, especially in the legs or abdomen
- Unusual tiredness, weakness, confusion or irritability
- Reduced output with a feeling of being unwell, or very watery output that will not settle
If these appear, contact your stoma care nurse, GP or out-of-hours service. Early contact prevents most hospital admissions.
Diet and eating with an ileostomy
There is no single ileostomy diet. Most foods are fine, and unnecessary restriction does more harm than good. The two areas worth thinking about are blockage risk and hydration, with gas, odour and output thickness as secondary concerns.
Reintroducing food after surgery
Most teams start with light, low-fibre food and build up over a few weeks. Appetite is often poor at first and returns gradually. A dietitian attached to the surgical or stoma team can help if you are losing weight, struggling to eat, or have short bowel.
Foods that may cause a blockage
These are typically high-fibre foods with tough skins or fibrous strands that the small bowel can struggle to push through a narrow stoma:
- Raw celery, mushrooms, asparagus stems
- Sweetcorn skins, popcorn
- Nuts, seeds, dried fruit such as raisins, dates and apricots
- Coconut and coleslaw
- Whole apple skins, pineapple core
- Cabbage and leafy greens in large quantities
- Mango and orange membrane
These foods are not forbidden. The rules that matter are chew thoroughly, eat smaller portions, introduce new high-fibre foods one at a time, and stay well hydrated when eating them. People who wear dentures or who bolt their food are at higher risk.
Foods that may thicken output
Useful when output is loose or watery: bananas, applesauce, white rice, white bread, pasta, smooth peanut butter, boiled potato without skin, and marshmallows. These are traditional and widely used, though evidence for each is largely anecdotal.
Foods that may loosen output
Spicy food, caffeine, alcohol, very sugary foods and drinks including some fruit juices, and some high-fat fried foods. Sugar-free products containing sorbitol or similar sweeteners can also loosen output.
Gas and odour
Beans, lentils, broccoli, cabbage, onions and garlic commonly increase gas; eggs, fish and asparagus are often cited for odour; fizzy drinks add gas directly. Everyone’s tolerance is different, and a food diary for the first few months is a practical way to spot personal triggers without cutting out foods you enjoy.
A note on fibre and fluids together
High-fibre food without enough fluid is the classic recipe for a blockage. If you eat a fibrous meal, drink alongside it.
Pouching, emptying and skin care
Good pouching is the other half of living well with an ileostomy, alongside hydration.
How often to empty and change
Most people empty the pouch four to eight times a day — often before meals, before bed, and whenever it feels a third to half full. Emptying before it is full reduces the weight on the seal and the risk of a leak. The full pouching system is usually changed every two to four days, taking five to ten minutes once a routine is established. Some people change more often; some less. Your stoma care nurse can advise on a schedule that suits your skin and output.
Keeping the skin healthy
The skin around a stoma should look like the skin anywhere else on your body — intact and unbroken. Any redness, weeping, itching or soreness in the ring of skin under the adhesive is a warning sign, usually caused by output getting underneath. The answer is almost always a better-fitting pouching system rather than more adhesive: measuring the stoma, choosing the right opening size, and considering a convex system, a seal or paste, or a belt if the stoma is flush or retracted.
Never cut a pouch opening larger than the stoma ‘just in case’; exposed skin under the adhesive is skin that output can attack.
When pouching gets difficult
Difficult body shapes, dips, creases, a very flat stoma, or a stoma close to a scar can all make a reliable seal hard to achieve. This is exactly the kind of problem a stoma care nurse solves routinely — ask for a review rather than struggling with trial and error.
What complications should I be aware of?
Most ileostomies are uneventful for years. The conditions below are the ones worth recognising early.
Peristomal skin irritation
The single most common problem. Itchy, red, broken or weeping skin around the stoma is nearly always caused by leakage. Fixing the fit — often with a convex barrier, a different opening size, or a skin-protecting ring — usually resolves it within days.
Food blockage
Undigested fibrous food can partially or completely obstruct the small bowel near the stoma. Signs include cramping abdominal pain, watery output that then stops, a Swollen stoma, nausea, vomiting and a hard, tender abdomen. Your stoma care nurse may suggest measures such as a warm bath, gentle massage around the stoma, and sips of fluid — but do not attempt to irrigate or clear the stoma yourself. If pain is severe, if you are vomiting, or if there is no output at all, seek urgent medical help the same day.
Parastomal hernia
A bulge beside or behind the stoma, caused by abdominal contents pushing through the opening in the abdominal wall. Less common with ileostomies than with colostomies, but still possible, and more likely with heavy lifting, coughing or weight gain. Many hernias can be managed with support garments and advice; some need surgical repair.
Prolapse, retraction and stenosis
The stoma may lengthen (prolapse), sink below the skin surface (retraction), or narrow (stenosis) over time. Prolapse is more common with loop ileostomies. Most of these are managed conservatively with adapted pouching; a few need surgical revision.
Dehydration and electrolyte imbalance
Particularly low sodium and low magnesium, and the most common cause of readmission in the first weeks. Prevention is covered above; treatment may need fluids and electrolyte replacement under medical supervision.
Kidney injury
Repeated or chronic dehydration over years can damage the kidneys. This is why many teams arrange an annual review with blood tests, including kidney function, for people with an ileostomy. It is a good reason to take long-term hydration seriously rather than treating it as a first-few-weeks issue.
Vitamin B12 deficiency
The final section of the ileum absorbs vitamin B12. People who have had part or all of the terminal ileum removed — or who have had an ileoanal pouch — may need lifelong B12 replacement, usually by injection. If your ileum is intact, deficiency is less likely, but levels may still be checked.
Gallstones and kidney stones
Both are somewhat more common after ileal surgery. Gallstones occur because bile salt absorption into the blood alters bile composition; kidney (oxalate) stones become more likely when fat malabsorption increases oxalate absorption. Both are usually managed if and when they cause symptoms.
When to seek medical help
Contact your stoma care nurse, GP or surgical team if you notice any of the following:
- The stoma changes colour to dark purple, brown or black (seek urgent help immediately)
- No output together with abdominal pain, nausea, vomiting or a swollen stoma — possible blockage
- High output that does not settle — roughly more than 1.5–2 litres a day for more than 24 hours
- Signs of dehydration: dizziness, dark urine, muscle cramps, confusion
- Bleeding from inside the stoma, or more than a tiny trace when wiping
- Severe skin irritation that does not improve with your usual pouch adjustments
- Fever, chills, or feeling generally unwell
When in doubt, call. Early contact with a stoma care team prevents most hospital admissions. If you cannot reach your team and feel seriously unwell, use urgent care services rather than waiting.
Living with an ileostomy
The daily routine
Most people empty the pouch four to eight times a day — typically before meals and before bed — and change the whole system every two to four days. Output is often quietest overnight if you eat your main meal earlier in the evening. Within a few weeks the routine becomes automatic rather than a source of anxiety.
Clothing
A modern pouch lies flat and is invisible under ordinary clothes. Many people prefer high-waisted underwear or a light stoma wrap or support belt for extra security during exercise or on active days. Tight waistbands worn directly across the stoma are the main thing to avoid; a belt that sits above or below the stoma is usually comfortable.
Showering, swimming and bathing
The pouch is fully waterproof and can be worn in showers, baths, pools, the sea and hot tubs. Some people prefer to shower with the pouch off, which is also safe — the stoma itself can be rinsed with plain warm water. Soap residue can affect adhesion, so many people rinse the skin well afterwards and let it dry fully before reapplying.
Exercise and sport
Almost all exercise is possible with an ileostomy, including running, cycling, swimming, yoga, weight-training and many contact sports. Support belts and wraps help with confidence and reduce rubbing. Build up heavy lifting gradually over the first three months after surgery to reduce hernia risk, and drink more than usual during and after exercise, since sweat losses are added to stoma losses.
Travel
People with ileostomies travel widely, including long-haul flights and remote destinations. Practical tips:
- Carry supplies for at least double the length of the trip, and keep at least one full change in hand luggage
- Carry an ostomy travel certificate for airport security; most national ostomy associations publish a template
- Plan ahead for extra hydration, particularly in hot or high-altitude destinations and on long flights
- Identify a pharmacy or clinic near your destination in case you need supplies or advice
- Remember that dehydrated, salty airline food and disrupted routines can both affect output
Sex and intimacy
An ileostomy does not prevent a normal, satisfying sex life. Confidence often takes a few months to rebuild, and both physical and emotional factors are involved — surgery in the pelvis can temporarily affect erectile function and ejaculation in men, and vaginal dryness or discomfort in women. Intimacy wraps, pouch covers, and open communication with a partner all help. Specialist counselling is widely available through stoma care nurses and ostomy associations, and it is worth asking for rather than waiting.
Work
People with ileostomies work in every field, from office roles to manual trades and emergency services. Most return to office-based work within four to eight weeks and to physical work within eight to twelve weeks. Employers are usually supportive when given clear, practical information about what you need — a private space to change, time for appointments, and understanding that heavy lifting may need modifying. Ostomy associations publish workplace guides for both employees and managers.
Emotional wellbeing
It is normal to feel grief, anger or shock after stoma surgery, even when the operation was planned and welcome. Most people adjust over the first year, and many describe a marked improvement in quality of life once a painful, unpredictable illness is behind them. If low mood, anxiety or body-image distress persist, talk to your GP, your stoma care nurse or a clinical psychologist — this is a recognised part of recovery, not a weakness.
Reversal: when ileostomies are temporary
A temporary loop ileostomy is reversed once the surgical join below it has healed — usually three to twelve months after the original surgery, confirmed by imaging or a flexible camera study such as a sigmoidoscopy or pouchoscopy.
What reversal involves
Reversal is usually a smaller operation than the original surgery, performed through the stoma site or with keyhole incisions, with a hospital stay of two to five days. The bowel is rejoined and the abdominal wall closed. Your stoma nurse will discuss how to prepare and what to expect.
After reversal
Stool returns to passing through the rectum and anus, but bowel habits often take several months to settle, and frequent or urgent stools, soreness and a need to be near a toilet are common in the early weeks. Anti-diarrhoeal medicines are sometimes used, on medical advice. People who have had a J-pouch built often have four to eight bowel movements a day long-term, which most describe as a good quality of life — though some develop pouchitis and need treatment.
A permanent end ileostomy is created when the colon and rectum have been removed and reconstruction is not appropriate. Long-term outcomes are excellent for most people, and many describe the operation as the single best thing they ever did for their health, particularly after years of severe ulcerative colitis or Crohn’s disease.
Support and community
You do not have to navigate this alone. Trusted resources are widely available and usually free of charge:
- Stoma care nurses at your hospital or in the community — your most useful long-term resource
- National ostomy associations in your country — most run helplines, peer-support visitor programmes and local meet-ups
- IBD patient organisations, if your ileostomy was created for ulcerative colitis or Crohn’s disease — disease-specific information, peer connection and lifestyle advice
- Online peer communities for day-to-day questions and shared experience
- Specialist counselling through hospital teams or community mental-health services if emotional adjustment is harder than expected
Talking to a peer-support visitor who has lived well with an ileostomy is one of the most useful steps for anyone newly diagnosed, and you can usually request one through your stoma care nurse.
The bottom line
An ileostomy is a surgical opening of the small intestine to the abdominal wall, created to bypass a diseased, damaged or removed colon. It is a cornerstone of modern surgical treatment for severe inflammatory bowel disease, hereditary polyp syndromes and some cancers — and for the great majority of people, life with a well-fitting ileostomy is full, active and comfortable.
The two practical priorities are good pouching (a well-fitting system, reviewed by a stoma care nurse as your body changes) and good hydration (enough fluid, a normal amount of salt, and an oral rehydration solution plan in place before you need it). With those in place, almost everything else is normal life.
This article is general information and cannot replace personal advice. Always speak to your stoma care nurse, GP or specialist team about your own stoma, output, diet and medicines.
Free guide
The New Ostomy Patient Guide
Everything for the first weeks with a stoma — pouching, skin care, diet, and getting back to daily life. Written with stoma care nurses. Free, by email.
Common questions
Frequently asked questions
- Does having an ileostomy shorten your life?
- No. An ileostomy is a diversion, not a disease, and most people live a normal lifespan with one. Outcomes are generally driven by the condition that led to surgery rather than by the stoma itself — and for many people with severe inflammatory bowel disease, health improves markedly once the diseased bowel is removed. The main long-term risk to protect against is chronic dehydration and its effect on kidney function, which is why routine blood tests are worthwhile.
- Will other people be able to tell I have an ileostomy?
- In practice, almost never. A well-fitting modern pouch lies flat and sits under ordinary clothing, and the appliance itself is odour-proof while it is intact. Pouch gas can make a quiet fluttering or gurgling sound, and the stoma itself makes no noise. Odour is only an issue if a seal has failed; if you notice leakage or persistent odour, that usually signals a fit problem for your stoma care nurse to review.
- Can I get pregnant and have a baby with an ileostomy?
- Yes — most women with an ileostomy conceive and carry a pregnancy normally, and the stoma does not prevent vaginal delivery in most cases. Fertility can be affected by previous pelvic surgery, and some women with an internal pouch have reduced fertility compared with those who have an ileostomy, so this is worth discussing before you plan a pregnancy. A pregnancy with a stoma is usually managed jointly by obstetric and stoma care teams, and the pouch may need refitting as the abdomen changes shape.
- Do tablets and medicines still work if I have an ileostomy?
- Most medicines are absorbed well, because the stomach and the upper small intestine are untouched. The exceptions tend to be modified-release, slow-release, enteric-coated or 'once-daily' tablets, which may pass through too quickly to release their full dose. Always tell your pharmacist and prescriber that you have an ileostomy so alternative formulations can be considered. Laxatives and some fibre supplements are usually inappropriate and should only be used on medical advice.
- Can an ileostomy be reversed years later?
- It can, but the decision depends on why it was made and what remains downstream. A temporary loop ileostomy is normally reversed within about three to twelve months, once healing is confirmed. A permanent end ileostomy created after removal of the colon and rectum cannot be reversed as such, although in selected cases reconstructive options such as an internal pouch may still be discussed with a specialist surgical team. Reversal after a long interval carries more risk and needs individual assessment.
References